A urethral stricture is a narrowing of the urethra, the tube that carries urine out of the body. Its two standard treatments lie at opposite ends: internal urethrotomy, a simple procedure that often provides only short-term relief, and urethroplasty, a more durable but demanding operation available at few centres. My post makes the case for the drug-coated, or medicated, balloon, which I hope will offer men an option in between.
What is a urethral stricture?
In a stricture, scar tissue builds up in the wall of the urethra. The blockage can range from mild to severe. At its worst, the urethra closes completely, and the kidneys can lose function.
Anterior strictures occur in the penile and bulbar urethra, the front part of the urethra. Posterior strictures occur deeper, in the membranous and prostatic urethra. Strictures affect men in their productive years and often persist for years.
There are many causes, so there is no single answer. Strictures can result from medical treatment, infection or inflammation, or injury. Causes and risk factors include radiotherapy to the pelvis or urinary diversion surgery, injury, a broken pelvis, congenital abnormalities, stones, certain cancers, catheter insertion, prostate surgery, benign enlargement of the prostate, untreated or recurrent urinary infection, and sexually transmitted infections such as gonorrhoea or chlamydia.
How does a stricture show itself?
Many symptoms relate to urine flow: a weak or slow stream, difficulty passing urine, frequent or urgent urination, pain when urinating, and leakage. Other symptoms include blood in the semen, dark or bloody urine, reduced urine output, lower abdominal pain, and enlarged or tender lymph nodes in the groin. Some men develop urinary retention, meaning they cannot pass urine, or a distended bladder.
The main test is a retrograde urethrogram (RGU), an X-ray of the urethra using contrast dye to map the stricture. Other tests may include a urine test, a urine flow test, a cystogram, ultrasound of the urethra and pelvis, and an MRI scan of the pelvis. Cystoscopy is an internal examination using a thin telescope.
What are the two standard treatments?
In internal urethrotomy (VIU), the stricture is cut through a telescope passed up the urethra. It is simple, easy to learn, widely available, cost-effective, and associated with a short recovery. Its benefit is often brief, especially when the stricture has recurred, and when it fails, it leaves dense scarring.
Urethroplasty is a surgical procedure to reconstruct the urethra. It is more likely to succeed in the long term, and if the stricture returns, it causes less scarring. However, the operation takes surgeons a long time to learn, is offered at few centres, requires expertise and a steady volume of cases, and can have serious complications.
Each option resolves one half of the problem and creates the other. The review I cite notes that a first short bulbar stricture treated via the scope succeeds in about 60% of men over one to two years; that success falls sharply with each repeat and approaches zero after a third attempt; and that repeated treatment fails in up to 80%.
How does the medicated balloon work?
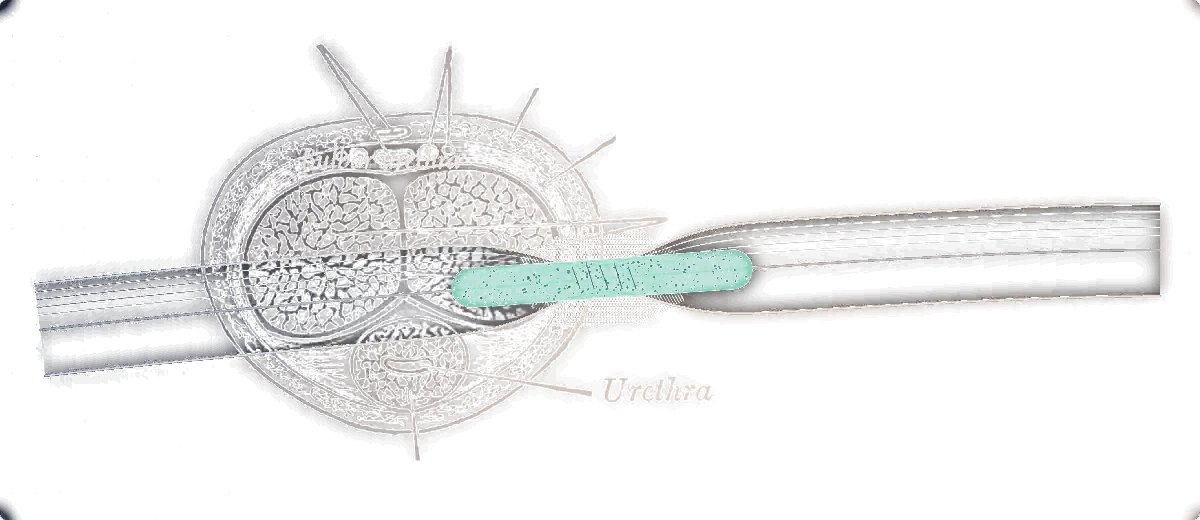
The procedure is similar to an ordinary balloon dilation. The balloon is placed across the stricture and inflated, which opens the narrowing and creates tiny cracks in the scar. Its coating delivers paclitaxel, a drug that inhibits cell division and growth, into those cracks. The aim is to prevent the stricture from recurring.
In Elutax, the balloon's coating has two layers of dextran and one layer of the drug paclitaxel. The dextran binds paclitaxel firmly to the cracks created by the expanding balloon.
In the technique I describe, the patient receives a general or spinal anaesthetic. Cystoscopy and X-ray together ensure the balloon opens exactly at the stricture. A very tight stricture is first opened with a urethrotomy to prevent the drug from being wiped off the balloon. The balloon remains inflated for five minutes, and a catheter remains in place for five days.
Follow-up is part of the treatment. In my protocol, a condom is used as a barrier for six months, and conception is not planned for six months. Regular checks continue for three years, as most strictures recur within that period. Each visit includes assessment of symptoms, a urine flow test and an ultrasound of residual urine in the bladder, with a urethrogram if needed.
Who does it suit, and what are its limits?
Selection determines the outcome. The balloon suits a stricture that is short, soft and still open. Short means ideally under 2 cm in the bulbar urethra, and never over 3 cm. Soft means the scarring is not very dense, and open means the urethra is narrowed but still has a channel through it. A complete blockage with dense scarring is not suitable for balloon treatment.
The advantages I list are that it is easy to use and quick to learn, and that in the trials of Optilume, another paclitaxel-coated balloon, more men remained free of further treatment than after urethrotomy or dilation. The review I cite reports mostly mild, short-lived side effects, such as blood in the urine, burning when passing urine, and urinary infection. Its limitations include higher cost, long strictures, very dense scarring, allergy to paclitaxel, failure when the technique is poor, and the need for long-term follow-up.
What do I hope for it?
As I wrote in June, I hope that an intermediate therapy such as medicated balloon dilation offers a good chance for these patients. I see it as a genuine middle path between a procedure that does not last and one that few can offer. The review I cite offers a balanced verdict: drug-coated balloons are a promising option that reduces repeat dilations and urethrotomies, but urethroplasty remains the gold standard for recurrent or complex strictures.
The same balloon is also used in ureteric strictures, where, for many patients, major reconstruction remains the only option at present. The early results are promising, but the evidence is limited and further trials are still needed. My talk also describes its use there as off-label, meaning outside its approved uses.
If you have a weak stream or a stricture that keeps recurring, please see a urologist so the cause can be found.
What should referring physicians know?
The trial evidence in my talk concerns the Optilume paclitaxel-coated balloon. ROBUST I was a single-arm, open-label, industry-sponsored trial in men with recurrent bulbar strictures, with a mean length of 0.9 cm (up to 2 cm), a lumen under 12F, and excluding those with radiation, lichen sclerosus, or previous urethroplasty. At five years, IPSS had fallen from 25.2 to 7.2 (P < .001), Qmax had risen from 5 to 19.9 mL/s (P < .01), and post-void residual had fallen from 141.4 to 59.5 mL (P < .01). Erectile function was unaffected; there were no serious treatment-related adverse events; and 71.7% were free from further intervention through five years (Kaplan-Meier). In the bulbar urethra, the 30F balloon performed better than the 24F, and success did not depend on stricture length or prior treatment.
The review I cite supports the use of the balloon for recurrent bulbar strictures under 3 cm, particularly in men unsuitable for urethroplasty. Durability is uncertain for longer or more complex strictures, and other parts of the urethra still need study. My technical points: never touch the balloon surface, size it at least 20 mm longer than the stricture so it extends 10 mm beyond each end, inflate to 8 atm for 5 minutes, and leave a 14F all-silicone Foley in place for 5 days.